

By the end of this hands-on guide you will confidently locate and stimulate the main pressure points for neck, understand which acupuncture points on the neck may be needled, and be able to run safe 10–30 minute acupressure sessions or prepare a professional-style acupuncture plan. Expect 30–90 minutes to learn and 10–30 minutes per self-treatment; skill level: beginner to informed self-care (not a substitute for clinical training).
Before you start
- Prerequisites: no active infection, no fever, not within 24 hours of heavy anticoagulant dose, not pregnant without practitioner approval.
- Tools & materials for acupressure: clean hands, short trimmed nails, a soft towel, small tennis ball for trigger-point release, timer (10–30 minutes).
- Tools & materials for practitioners/needling: single-use sterile acupuncture needles (0.12–0.30 mm × 15–40 mm), sterile swabs, disposable gloves, sharps container, treatment couch, informed consent form, emergency contact list.
- Workspace: comfortable seated or prone position, neck supported with a small pillow, well-lit environment.
Understanding Neck Pain and Its Relation to Pressure Points
Neck pain ranges from short-lived muscular tension to chronic degenerative and radicular conditions. Anatomically, the neck contains vertebrae C1–C7, the upper thoracic junction, multiple muscles (upper trapezius, levator scapulae, sternocleidomastoid), cervical nerve roots and the carotid and vertebral vessels. Pain sources include muscle strain, facet joint irritation, disc pathology and referred pain from thoracic or cranial structures.
Traditional Chinese Medicine (TCM) explains many neck complaints as blockages or imbalances in the neck meridians — most notably the Bladder meridian running bilateral along the spine and the Gallbladder meridian crossing the posterior neck base. In practice, we treat both local neck points and distal points (hands, feet, shoulders) to modulate nociception and restore balanced qi flow. Define terms: a meridian is an energetic channel; an acupoint is a defined location on that channel; qi refers to functional energetic movement. Think of pressure points as local “release valves” and acupoints as “energy gates” that, when stimulated, alter muscle tone and pain signalling.
Physiologically, acupuncture and acupressure modulate neck pain via three overlapping mechanisms: local mechanical effects (trigger-point relaxation), segmental spinal gate control (reducing pain transmission at the dorsal horn), and central descending inhibitory effects (release of endorphins, modulation of neurotransmitters). According to a 2018 individual-patient meta-analysis in JAMA Internal Medicine, acupuncture produced clinically meaningful reductions in chronic pain compared with sham and standard care; for neck-specific outcomes, a 2023 literature review found mixed but generally positive short-term benefits (see evidence section below). 2018 IPD meta-analysis (JAMA Internal Medicine) and 2023 systematic review search results.
Common neck pain presentations that respond to point therapy:
- Acute muscle spasm after poor posture or sudden movement (hours–days).
- Chronic tension and myofascial trigger points (weeks–months).
- Cervicogenic headache and referred pain to the occiput and shoulders.
- Persistent pain after whiplash where mechanical and neurological drivers coexist.
Clinical rationale for point selection: local points reduce muscle tone and restore range; distal points modulate systemic pain pathways and autonomic balance; meridian-based points address broader functional patterns (e.g., Bladder meridian points for stiffness along the back of neck/upper thoracic spine).
Transition: now that we’ve covered anatomy, physiology and TCM context, we’ll locate the exact points used most often for neck pain and how to find them reliably.
Key Pressure Points and Acupuncture Points for Neck Pain Relief

Below is a practitioner-focused numbered list of the most reliable points used for neck pain treatment. Each entry includes the TCM name, common clinical name, clear anatomical location, meridian association, technique (acupressure vs needle), typical depth/angle for needling, benefit, and safety notes.
-
GB20 — Fengchi (Wind Pool)
Location: in the hollow between the upper portion of the sternocleidomastoid and the trapezius at the base of the skull approximately 1–2 fingerbreadths lateral to the external occipital protuberance. Meridian: Gallbladder.
Use: excellent for occipital and upper cervical muscle tension, cervicogenic headache, visual disturbance due to neck tension.
Acupressure: press with thumbs or index fingers 30–60 seconds, repeat 3 times. Needle technique: perpendicular or slightly oblique insertion toward the skull base, 0.5–1.0 cun (5–10 mm) depth for thin patients, up to 1.5 cun (15 mm) in larger necks; angle shallow to avoid occipital vessels. Retain 20–30 minutes. Safety: avoid deep posterior-superior insertion to prevent puncturing suboccipital tissues; if unusual numbness appears, withdraw needle immediately. -
BL10 — Tianzhu (Celestial Pillar)
Location: 1.3 cun lateral to the posterior midline, in the trapezius hollow just below the occiput (at the lateral aspect of the trapezius insertion). Meridian: Bladder.
Use: relieves stiffness across the upper trapezius and back of neck, reduces shoulder-neck referral pain.
Acupressure: firm circular kneading for 45–90 seconds; for needling, insert obliquely medially or slightly upward 0.3–0.6 cun (3–6 mm) to avoid deep structures. Safety: avoid direct posterior deep insertion; palpate for tenderness rather than blindly inserting where pain is vascular. -
SI15 — Tianzhong (Middle Shoulder)
Location: 2 cun lateral to the lower border of the spinous process of C7, on the upper scapular/neck region near the medial shoulder border. Meridian: Small Intestine.
Use: reduces stiffness between neck and shoulder, useful for trapezius trigger points.
Acupressure: sustained pressure 20–45 seconds, then circular strokes. Needle: perpendicular insertion 0.5–1.0 cun (5–10 mm). Safety: watch for deep insertion toward lung apex; in thin patients, use shallower depth. -
GB21 — Jianjing (Shoulder Well)
Location: midpoint between C7 and the acromion on the highest point of the shoulder. Meridian: Gallbladder.
Use: powerful for acute neck and shoulder tension and restricted neck rotation; widely used for trapped neck/shoulder pain.
Acupressure: apply steady pressure with thumb for 30 seconds, avoid overly intense force. Needle: perpendicular insertion 0.5–1.0 cun, avoid deep insertion angled toward the thorax. Safety: STRICT CONTRAINDICATION during pregnancy (may induce uterine contractions); caution with thin patients (risk of pneumothorax is small but real if insertion slants inferiorly). -
LI4 — Hegu (Joining Valley)
Location: dorsum of the hand between the first and second metacarpal bones, at the high point of the muscle when the thumb and index finger are opposed. Meridian: Large Intestine.
Use: distal analgesic point commonly used to reduce neck pain by activating descending pain control. Excellent as an adjunct for tension-related neck pain and headaches.
Acupressure: firm thumb-pressure for 30–60 seconds per side, repeat 2–3 times. Needle: perpendicular insertion 0.5–1.0 cun. Safety: avoid in pregnancy (some practitioners avoid LI4 due to uterine activity concerns). -
GB20/BL11 Combination (Occiput–Upper Spine)
Location: bilateral GB20 plus upper thoracic Bladder line points (BL11/12 region). Meridian: Gallbladder and Bladder.
Use: pairing local occipital points with upper back bladder points releases spinal tension and improves mobility across the cervicothoracic junction.
Technique: combine 30–60 seconds acupressure at GB20 with rocking kneading at BL11 for 60–90 seconds. Needling: BL11 shallow 0.3–0.5 cun. Safety: palpate before needle; avoid deep insertion over the spinous processes. -
SI16 / SI17 — Cervical Anterior Line (Use cautiously)
Location: SI16 is on the posterior border of the sternocleidomastoid (SCM) near the lateral throat, SI17 near the angle of the mandible. Meridian: Small Intestine.
Use: for radiating neck pain and stiffness that involves SCM referral patterns. Excellent when tension includes anterior neck structures.
Technique: very light acupressure with fingertips 20–30 seconds; needling is reserved for experienced practitioners due to proximity to carotid sheath—if used, shallow lateral insertion under ultrasound or by palpation with extreme care. Safety: do not needle SI16/SI17 unless trained; risk to carotid artery and jugular structures. -
Deck points: DU14 / GV14 — Dazhui
Location: midline, below the spinous process of C7 (prominent vertebra where neck meets upper back). Meridian: Du (Governor Vessel).
Use: calms systemic tension and reduces upper thoracic stiffness; often part of a segmental treatment plan for neck pain.
Technique: compress with thumbs for 20–45 seconds. Needle: perpendicular insertion 0.3–0.5 cun. Safety: avoid forceful deep needling. -
Trigger-point local spots — myofascial knots
Location: variable — commonly mid-upper trapezius, levator scapulae insertion near the superior medial border of scapula and along the posterior neck muscles.
Use: direct mechanical release of palpable knots reduces nociceptor activity and restores range of motion.
Technique: ischemic compression with thumb 20–90 seconds then slow release; small circular friction with 30–60 seconds of pressure. Needle technique (dry needling/acupuncture): short 10–20 mm perpendicular or oblique insert to the palpable taut band; manipulate gently to elicit local twitch response. Safety: ensure sterile technique; avoid needling too deep near lung apex. -
Distal balancing points — ST36 (leg), LV3 (foot)
Location: ST36 on lateral anterior lower leg; LV3 on the dorsum of the foot between 1st and 2nd metatarsals.
Use: systemic analgesic and regulatory points used to strengthen qi, reduce pain sensitivity and support long-term recovery when combined with local neck points.
Technique: 1–2 minutes of firm pressure or needle 0.5–1.5 cun depending on limb thickness. -
Occiput–neck junction points — small accessory points
Location: small unnamed points in the suboccipital triangle (medial to GB20) and along the posterior aspect of the SCM.
Use: fine-tuning mobility and releasing tight suboccipital muscles that commonly trigger headaches.
Technique: gentle transverse friction and 20–60 seconds of static pressure; needling only by experienced practitioners with shallow insertion. -
Bladder meridian line points (upper thoracic Bladder sequence)
Location: on the paraspinal line from upper thoracic to cervical areas — BL10, BL11, BL12, BL13 patterns over the back of the neck/upper thorax.
Use: treat the “spinal column” energetic aspect of chronic stiffness; stimulates segmental relaxation and autonomic balance.
Technique: sequential acupressure along 3–6 points for 2–3 minutes total; needling typically shallow 0.3–0.8 cun per point.
12 meridians chart -
Accessory distal points for headaches — Yintang / Taiyang
Location: Yintang (between the eyebrows) and Taiyang (temple region). Meridian: extra point and small intestine/bladder adjuncts.
Use: when neck pain is linked to frontal or temporal headaches; used as adjuncts for rapid symptomatic relief.
Technique: gentle circular pressure 30–60 seconds; needles shallow 0.2–0.5 cun. -
When to combine shoulder and neck points — GB21 + SI15 + BL10 pattern
Application: for restricted neck rotation with shoulder elevation; start with GB21 for shoulder release, follow with SI15 for scapular groove release, and finish with BL10 to restore occipital mobility.
Rationale: a pattern-based approach addresses the kinetic chain rather than isolated neck segments.
back acupuncture points chart
Clinical note: Always palpate and reproduce the patient’s familiar pain pattern before needling; a point that reproduces familiar pain often yields a stronger therapeutic response. Use distal points (LI4, ST36, LV3) to enhance analgesia and longevity of effect.
Transition: next, we translate these point locations into clear, replicable needling steps and clinical techniques including insertion depths, angles and manipulation methods.
How Acupuncture Needles Are Used for Neck Pain: Placement and Techniques
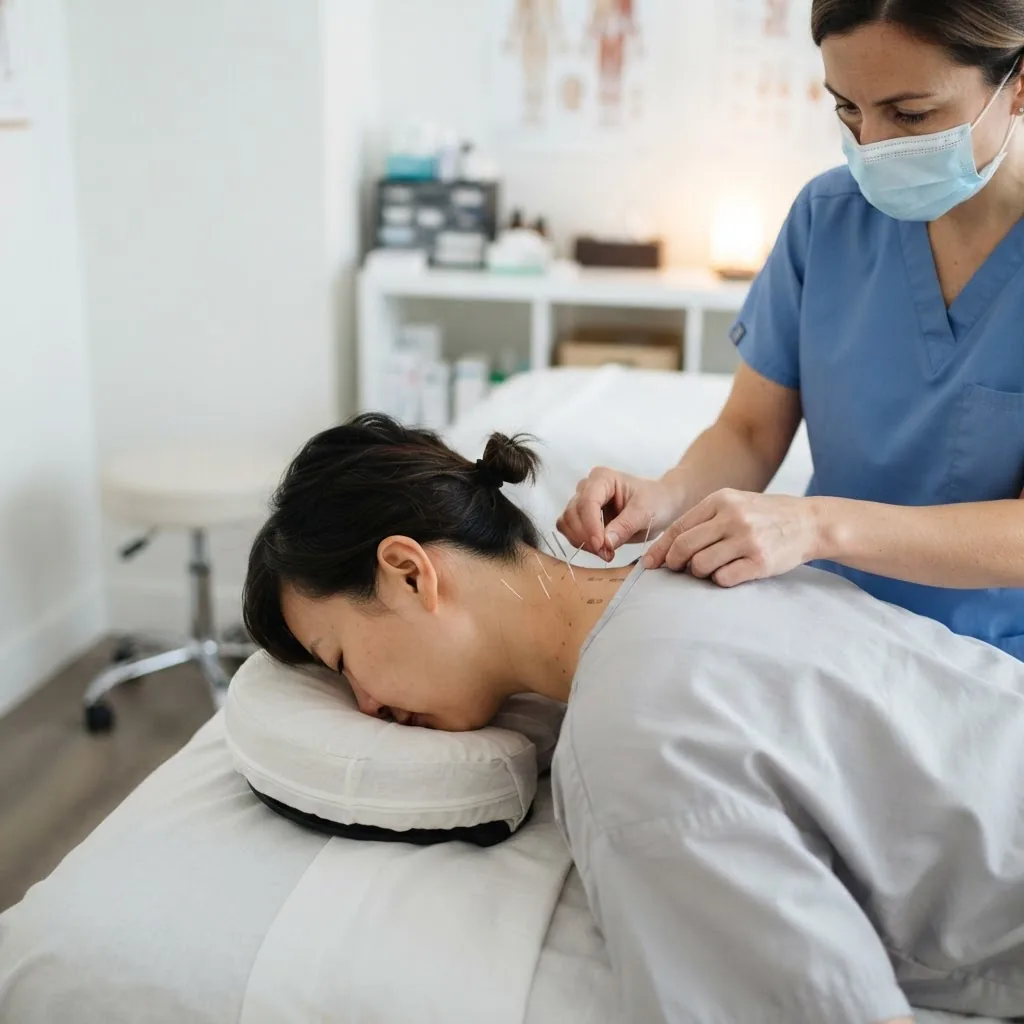
Below is a step-by-step how-to for needling common neck points safely. These instructions assume the practitioner is trained — do not needle without certification. For self-care use acupressure steps in the next section.
- Prepare the patient and environment. Confirm informed consent, medical history (anticoagulants, pacemaker, pregnancy, prior neck surgery). Position patient prone or seated with neck supported. Time allotment: 30–90 minutes total including assessment. Disinfect point areas with 70% isopropyl swab and allow to air dry 10–15 seconds.
- Palpation and point confirmation. Palpate and mark points that reproduce the patient’s familiar pain. Use single-finger palpation and compare bilaterally. Count cun measurements when locating classic points (use patient’s thumb width as a quick guide). Confirm no bruits or abnormal pulsations near planned anterior neck points (avoid if present).
- Select needle size and angle. Typical needles for neck: 0.18–0.25 mm × 25–40 mm for GB20/BL10; 0.12–0.20 mm × 15–25 mm for small accessory and distal points. Angle guidelines: GB20 perpendicular or 10–20° medially; BL10 oblique medially 10–30°; SI15 perpendicular 10–20°. Depth ranges: 0.3–1.5 cun (3–15 mm) depending on patient build — prefer shallower on thin patients. Always err shallower near major vessels and airway structures.
- Insert with controlled motion and watch for deqi. Use a smooth, decisive insertion to patient tolerance. Deqi (sensation of heaviness, aching, distension) indicates appropriate activation for many protocols; in the neck, avoid strong manipulations that cause radiating numbness or dizziness. If the patient reports pins-and-needles, withdraw slightly and retest.
- Needle manipulation techniques. Use subtle lifts and thrusts or gentle twirling (clockwise/anti-clockwise) for 10–30 seconds to elicit deqi. For muscle trigger points, short manipulations to produce local twitch responses can be effective; stop after one or two twitches to reduce soreness. Document which manipulation produced a response.
- Retention time and monitoring. Standard retention: 20–30 minutes. For acute muscle spasm, 10–15 minutes with repeat session within 48 hours may be more effective. Check patient comfort every 5–10 minutes; watch for vasovagal signs (pallor, sweating, nausea). If present, remove needles slowly and lay patient flat.
- Needle removal and immediate aftercare. Remove needles with a steady pull, press the site with sterile gauze for 5–10 seconds. Apply light adhesive plaster if bleeding occurs. Advise patient to rest 10–20 minutes post-treatment and hydrate. Expect mild transient soreness or bruising in <10% of insertions.
- Documentation and follow-up plan. Record points used, needle sizes, angles, depth, deqi response, retention time and any adverse events. Typical frequency: 1–2 sessions per week for 4–8 weeks for most chronic neck pain; reassess after 4 sessions. According to a 2018 IPD meta-analysis, a course of 6–12 sessions often yields measurable benefit for chronic pain conditions. JAMA Internal Medicine meta-analysis.
- Special techniques and adjuncts. When treating severe muscular knots, combine local needling with 30–120 seconds of ischemic compression pre- or post-needling. Consider electroacupuncture at low frequency (2 Hz) across paired neck points for persistent radicular or chronic pain—start at low amplitude and titrate to patient comfort. Use ultrasound guidance for deep cervical needling in anatomically complex cases.
- Safety checklist before each insertion. Confirm sterile packaging intact, single-use needles, no local infection, patient has eaten lightly (to reduce vasovagal risk), and emergency kit present. If treating near anterior neck structures (SI16/SI17/ST9), ensure visualisation or ultrasound; if uncertain, select safer posterior points instead.
Evidence and standards: Professional bodies recommend adherence to clean needle technique and documentation. For clinical evidence, review major analyses and guidelines: National Center for Complementary and Integrative Health (NCCIH) overview for acupuncture (NCCIH) and the Australian Acupuncture & Chinese Medicine Association standards (AACMA).
Transition: for non-needling self-care or immediate home relief, follow the step-by-step acupressure protocol next.
Acupressure Techniques for Neck Pain Therapy: Step-by-Step Guide
This section is a practical self-treatment routine you can apply safely at home. Each step lists durations, pressure levels, and positions.
- Sit upright with lumbar support and head neutral. Position: seated, feet flat, support under lower back; time: 1 minute to settle. Neck position: neutral, chin parallel to floor.
- Warm the neck tissues. Use a warm towel (38–40°C) applied to the posterior neck for 3–5 minutes to increase circulation and reduce guarding.
- Locate GB20 (both sides). Use fingertips to find the hollow at the base of the skull 1–2 fingerbreadths from midline. Apply thumb pressure, 30–60 seconds per side, firm but tolerable (~3–5/10). Repeat twice. If dizziness occurs, stop and rest.
- Press BL10 and trapezius insertion points. Use the index finger to apply steady pressure at BL10 for 30–45 seconds per side. Then follow the upper trapezius towards GB21 with kneading motions for 45–90 seconds.
- Ischemic compression on trigger points. Identify the most tender spot in the trapezius or levator scapulae. Apply direct pressure with the thumb until tenderness reduces by about 50% (hold 20–90 seconds). Release slowly; repeat once. Avoid excessive pain — target moderate strong pressure but not sharp pain.
- Use cross-fiber friction and gentle stretching. After compression, use circular friction for 30 seconds and gently rotate the neck within a pain-free range 5–10 times each direction. Hold stretches 15–30 seconds, repeat twice.
- Stimulate distal points for systemic effect. Press LI4 (hand) and LV3 (foot) for 30–60 seconds each to enhance analgesia. For self-application to LI4, use the opposite thumb and index finger and increase pressure to moderate intensity.
- Finish with calming holds and breathing. Lightly hold GB20 and GV14 for 60 seconds while instructing slow diaphragmatic breaths (6–8 breaths). Stand up slowly and re-assess pain and mobility.
- Frequency and progression. For acute pain: repeat protocol 1–3 times daily for 3 days then reduce frequency. For chronic pain: 1–2 daily sessions for 2 weeks then taper to maintenance 2–3 times weekly. If improvement plateaus after 4–6 weeks, consult a practitioner.
Practical tips: apply pressure for 20–90 seconds per point; use the patient’s thumb width as a quick “cun” measurement; avoid pressing over thyroid, carotid, or inflamed skin; stop if numbness or radiating tingling increases.
Common mistakes and how to avoid them (from practitioner experience)
I’ve seen three recurring errors: 1) placing needles too deep in thin-necked patients — I now measure and use shallower depths (0.3–0.6 cun) and confirm with palpation; 2) over-pressing GB21 in pregnant patients — I always screen for pregnancy and use alternative distal points instead; 3) ignoring systemic contributors — I used to treat only local knots, but combining LI4 and ST36 consistently gives longer-lasting relief.
Safety, Precautions, and When to See a Professional
Acupuncture and acupressure on the neck are effective when performed correctly but carry specific risks. Below are concise contraindications, red flags and referral suggestions.
- Contraindications (do not needle): active infection at the site, unregulated anticoagulation therapy with INR >3, local malignancy, uncontrolled psychiatric symptoms interfering with consent.
- High-risk anatomy to avoid for novices: anterior neck (carotid sheath, thyroid), deep lateral neck near jugular, and points immediately over major blood vessels.
- Pregnancy cautions: avoid GB21 and some strong distal obstetric points (discuss with practitioner).
- Red flags requiring immediate medical review: progressive neurological deficit (weakness, dropped arm), severe unrelenting night pain, fever with neck stiffness, new-onset severe headache with neck pain.
- Sterility and training: only clinicians trained in clean needle technique should perform neck needling. As a next step for training, consider the acupressure practitioner course or formal acupuncture certification.
Acupuncture Acupuncturist Training and Certification Guide is the recommended pillar for anyone seeking professional competence in needling technique and scope of practice. acupuncture therapy research and standards should be reviewed prior to clinical practice.
Evidence references: According to a 2018 IPD meta-analysis in JAMA Internal Medicine, acupuncture produces clinically significant pain reduction compared with sham in chronic pain cohorts; a targeted 2023 literature review found short-term benefit for neck pain in many trials but heterogeneity across protocols (see PubMed results linked earlier). For regulatory standards, consult national bodies such as the Australian Acupuncture & Chinese Medicine Association (AACMA) and the NCCIH overview (NCCIH).
When to see a professional: if you have persistent pain >6 weeks despite self-care, neurological symptoms (weakness, numbness), or a history of cervical spine surgery, book a trained acupuncturist or medical practitioner for assessment and integrated care.
Integrating Neck Acupuncture and Pressure Point Therapy with Other Treatments
Point therapy works best as part of a multimodal plan. Combine local acupuncture and acupressure with physical therapy, posture retraining, ergonomic fixes and pharmacologic strategies when needed. Use evidence-based combinations for best outcomes.
Comparative considerations:
| Therapy | Best use for neck pain | Notes |
|---|---|---|
| Acupuncture | Moderate-to-severe or chronic neck pain; refractory myofascial pain | Requires trained clinician; evidence supports short–medium term benefit |
| Acupressure / self-therapy | Acute tension, maintenance, symptom relief between sessions | Safe and immediate; useful for self-management |
| Physical therapy / exercise | Biomechanical correction, strength and endurance | Combine with point therapy for lasting change |
| Medication (analgesics, NSAIDs) | Acute pain flares or to enable active rehab | Use lowest effective dose; coordinate with practitioner |
To expand training across body areas and understand comparative methods, review targeted sibling guides on acupressure and acupuncture applications: acupressure points for abdominal pain, acupressure points for knee pain, ankle acupressure points, or acupuncture for back pain. For related facial-neck referral patterns see facial pressure points chart.
Integration tips:
- Start with acupressure and posture correction for immediate relief; transition to acupuncture for persistent problems.
- Coordinate frequency: while self-applied acupressure can be daily, clinical acupuncture is usually 1–2× weekly early in treatment.
- Use targeted exercise to maintain gains: 10 minutes of cervical mobility and scapular stabilization twice daily.
Summary and Resources for Further Learning
Key takeaways: locate and stimulate GB20, BL10, SI15 and trapezius trigger points for direct neck release; use LI4/ST36 for distal analgesia; needle with shallow depth and small angles in the neck; maintain sterile technique and refer when red flags appear. Short-term evidence supports acupuncture for neck pain; combine therapies for durable outcomes.
Further resources and training links:
- Acupuncture Acupuncturist Training and Certification Guide — professional pathway and credentialing details.
- 12 meridians chart — visual guide for meridian mapping.
- acupuncture therapy research — curated literature and training overviews.
- Classical TCM texts: Huangdi Neijing translations and modern TCM textbooks (seek accredited sources and university programs).
Compact practitioner checklist
- Screening completed and informed consent signed.
- Palpation reproduces familiar pain at planned points.
- Needle size, angle and depth selected and documented.
- Sterile single-use needles and sharps disposal ready.
- Retention time set (20–30 minutes) and patient monitored.
- Post-care instructions documented and follow-up booked (1–2 weekly).
When to call in a professional
Call a trained acupuncturist or medical practitioner if pain persists beyond 6 weeks despite self-care, if you experience neurological deficits, severe radiating pain, or increased weakness/numbness. For complex cervical spine conditions (prior surgery, deformity, systemic disease) seek multidisciplinary review.




